






To evaluate the diagnostic accuracy of objective tests including Visual Evoked Potentials (VEP), pupillometry, and eye-tracking technologies in detecting ocular malingering among individuals suspected of fabricating visual impairments for secondary gain.
MethodsFollowing PRISMA guidelines, PubMed, Web of Science, Scopus, EMBASE, and Cochrane Library were searched until June 2025. Studies evaluating objective diagnostic methods for detecting ocular malingering that reported diagnostic accuracy metrics were included. Two reviewers performed data extraction and quality assessment using QUADAS-2.
ResultsTen studies from 1993 to 2017 with 20 to 222 subjects were included. Approximately half of the studies employed experimentally simulated malingering paradigms, while the remainder involved clinically suspected cases. VEP was the most frequently evaluated modality and showed high sensitivity across studies, although specificity varied.
Pattern-reversal VEPs showed effectiveness in adults and military conscripts, while step VEPs demonstrated 100% specificity in paediatric cases. Pupillometry and specialised colour vision tests achieved 80–94% sensitivity and specificity rates. Most studies showed low bias risk in index test and reference standard domains. These findings suggest potential utility of objective tools as adjuncts in clinical and medico-legal settings.
ConclusionObjective diagnostic measures demonstrate promising utility as adjunctive tools for detecting ocular malingering and may support clinical decision making by providing reproducible assessments that bypass voluntary patient control. However, heterogeneity in study designs limits generalisability. Future research should standardise protocols and validate findings across diverse populations.
Ocular malingering, defined as the intentional fabrication or exaggeration of visual impairments for personal gain, poses a significant challenge in clinical practice.1,2 Individuals may feign visual deficits to obtain financial compensation, avoid occupational duties, or gain other benefits.3,4 Malingerers may seek financial benefits such as compensation claims, fraudulent insurance payouts, or legal protection, as well as non-financial benefits like social sympathy or avoidance of occupational duties.5
Accurate detection of such deceptive behaviours is crucial to ensure appropriate patient care and the equitable allocation of healthcare resources. The prevalence of ocular malingering varies across different populations and age groups.1,6 While comprehensive epidemiological data are limited, certain studies provide insight into its occurrence. For instance, in the context of military conscription, the incidence of malingering, including ocular malingering, has been reported to be between 0.5% and 3% among conscripts.7 A clinical study conducted in India among patients presenting with visual complaints in the absence of any identifiable organic pathology reported a moderately high prevalence of ocular malingering, estimated at 52.6%.8
A common method used to simulate vision loss is giving inconsistent responses during visual acuity tests. Patients claiming total blindness often exhibit normal pupillary light reflexes, which is physiologically inconsistent with true blindness.9,10 In other cases, malingerers may memorise eye charts to give the impression of partial vision loss while having normal vision.11–13 Some may intentionally squint, blink excessively, or complain of symptoms like light sensitivity or headaches to strengthen their claims.11,12 Another condition often mistaken for malingering is psychogenic visual loss, where patients subconsciously experience visual impairment due to psychological stress, trauma, or conversion disorder.14 While this differs from deliberate malingering, it can complicate diagnosis and require a multidisciplinary approach for assessment.15
Factors influencing malingering include poor medical knowledge, low socioeconomic status, lack of concern for one’s condition, and minor injuries.4 Common symptoms include light sensitivity, ocular discomfort, blepharospasm, colour vision loss, and blurred vision.13 In many African regions, limited access to advanced diagnostic tools and a shortage of specialised eye care professionals complicates the detection of ocular malingering. These challenges can lead to misdiagnosis and inappropriate management of patients presenting with visual complaints.
Several studies have explored methods to detect ocular malingering and assess their effectiveness.13,16 For example, a study utilising pattern visual evoked potentials (VEPs) demonstrated their efficacy in evaluating objective visual acuity and discriminating malingerers.6 Another study assessed the clinical usefulness of grating acuity measured by sweep visual evoked potentials (sweep-VEP) in diagnosing psychogenic visual impairment and ocular malingering.17 These studies highlight the potential of objective measures in identifying feigned visual impairments. Additionally, as detection techniques improve, there is a growing number of identified cases, suggesting that the prevalence of malingering may be underestimated.18 Understanding how ocular malingering occurs is crucial for clinicians to develop objective and reliable diagnostic methods to differentiate true visual impairment from feigned cases.
By employing tests such as optical coherence tomography (OCT), visual evoked potentials (VEP), and electroretinography (ERG), eye doctors can assess physiological responses that are beyond conscious control, improving diagnostic accuracy.19,20 Given the potential consequences of undetected malingering, including misallocation of healthcare resources and compromised patient care, a systematic review of existing detection methods is warranted. The primary research question guiding this review is: "What is the diagnostic accuracy of objective measures in detecting ocular malingering among individuals suspected of feigning visual impairment?" The objectives include assessing the sensitivity and specificity of these methods, identifying gaps in current research, and proposing directions for future studies.
MethodsThis systematic review adhered to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines to ensure transparent and methodical reporting. The review protocol was registered on PROSPERO (registration number CRD420251065223).
Eligibility criteriaStudies were eligible if they involved adult or paediatric populations suspected of ocular malingering, including those with confirmed cases or malingering simulated by design. Studies comparing between malingering individuals and non-disputed patients, or healthy controls were also included. The focus was on studies that evaluated objective diagnostic methods for detecting ocular malingering. These objective tests included, but were not limited to, VEP, ERG, pupillometry, eye-tracking technologies. Studies were considered regardless of whether these objective tests were compared to subjective assessments, such as patient-reported symptoms, or to a control group. Comparisons with established gold-standard diagnostic techniques were also accepted. Included studies were required to report, or provide sufficient data to calculate, diagnostic accuracy metrics such as sensitivity, specificity, positive predictive value (PPV), negative predictive value (NPV), receiver operating characteristic (ROC) curves, and area under the curve (AUC). Only original research studies employing appropriate study designs were included. These designs included diagnostic accuracy studies, case-control studies, cross-sectional studies, and cohort studies.
Studies were excluded if they were editorials, opinion pieces, or reviews. Additionally, animal studies, studies lacking diagnostic accuracy data, or those not involving objective diagnostic tests for ocular malingering were excluded. This review was limited to studies published in English. The decision to apply this language restriction was primarily due to the practical challenges associated with accurately translating clinical and diagnostic terminology from other languages, which could compromise the integrity of data extraction and interpretation. We acknowledge that this restriction may introduce language bias and result in the exclusion of potentially relevant studies published in other languages.
Information sourcesThe following databases and resources were searched to identify relevant studies: PubMed, Web of Science, Scopus, EMBASE, Cochrane Library, Google Scholar, and grey literature sources such as dissertations, conference proceedings, and professional organisation reports.
The search was carried out to identify studies published from the inception of the database until June 2025, without geographical limits.
Search strategyThe search strategy combined key terms related to ocular malingering and objective diagnostic measures. Core concepts included “ocular malingering,” “visual malingering,” “non-organic visual loss,” and “functional visual loss,” alongside diagnostic modalities such as “visual evoked potential,” “VEP,” “pupillometry,” “eye tracking,” and “electroretinography.”
To enhance sensitivity, database-specific adaptations and expansions were applied, including electrophysiology-related terms such as “pattern-reversal VEP,” “pattern reversal VEP,” and “sweep VEP,” as well as broader diagnostic and forensic terminology relevant to ophthalmic assessment. These terms were adjusted according to the indexing structure of each database (e.g., MeSH terms in PubMed and Emtree terms in EMBASE). The third search string included “sensitivity” OR “specificity” OR “predictive value” OR “ROC curve”. Finally, all the search strings were combined using the Boolean operator “AND” and the results screened for the included studies.
Study selection processTwo independent reviewers (GO, CEA) extracted data to minimise errors. Disagreements during the screening process were resolved through discussion and consensus, with discrepancies resolved by a third reviewer (EEA). Titles and abstracts of remaining studies were screened against eligibility criteria. First, titles and abstracts were screened to exclude studies not of interest. Publications were then screened to confirm the inclusion criteria were met, and only full-text articles were left.
Data collection processTwo reviewers (PTA and PEA) extracted data from each eligible study using a standardised data extraction sheet and subsequently cross-checked the results. Prior to full data extraction, the form was pilot tested on a subset of included studies to ensure clarity, completeness, and consistency. Extracted data points included study characteristics (author, year, country, study design, type of malingering), population details (sample size, age range), diagnostic test used (VEP, perimetry, pupillometry), and outcome measures (sensitivity, specificity, predictive values, area under the curve [AUC]). Discrepancies in extracted data were resolved through discussion and consensus, with involvement of a third reviewer (EEA) where necessary.
Study risk of bias assessmentThe risk of bias in included studies were assessed using the Quality Assessment of Diagnostic Accuracy Studies-2 (QUADAS-2) tool,21 which evaluates four key domains: patient selection, index test, reference standard, and study flow and timing. Each study was classified as having a low, high, or unclear risk of bias based on these domains. This assessment helped determine the overall quality and reliability of the included studies, ensuring that findings were based on robust evidence. Two reviewers (DM and RP) independently performed the risk of bias assessment, with disagreements resolved through consensus and or arbitration by a third reviewer (EA).
ResultsStudy selectionThe comprehensive search of multiple databases and grey literature identified 232 records. After removing duplicates, 182 records were screened based on title and abstract. Following the screening process, 156 records were excluded because they did not meet the inclusion criteria. Of the 26 full-text articles assessed for eligibility, 16 were excluded because they were editorials, reviews, or studies that lacked diagnostic accuracy data. Consequently, we included 10 studies in the qualitative synthesis (Fig. 1).
Study characteristics
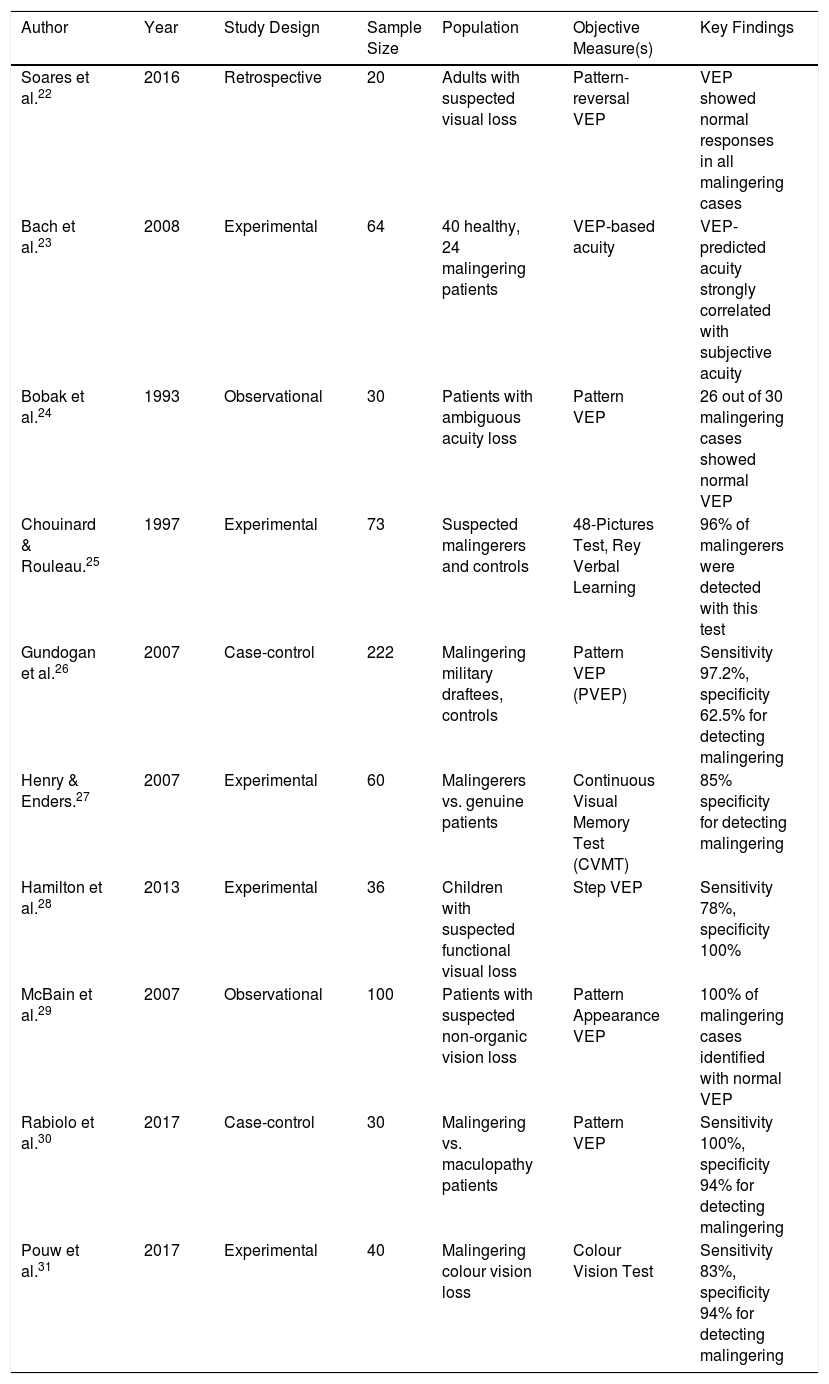
Table 1 presents the characteristics of the 10 included studies, which span from 1993 to 2017. The studies included sample sizes ranging from 20 to 222 subjects. The studies included in the review also varied in design with 1 retrospective study (10%), 5 experimental studies (50%), 2 observational studies (20%), and 2 case-control studies (20%).
Characteristics of the 10 included studies.
| Author | Year | Study Design | Sample Size | Population | Objective Measure(s) | Key Findings |
|---|---|---|---|---|---|---|
| Soares et al.22 | 2016 | Retrospective | 20 | Adults with suspected visual loss | Pattern-reversal VEP | VEP showed normal responses in all malingering cases |
| Bach et al.23 | 2008 | Experimental | 64 | 40 healthy, 24 malingering patients | VEP-based acuity | VEP-predicted acuity strongly correlated with subjective acuity |
| Bobak et al.24 | 1993 | Observational | 30 | Patients with ambiguous acuity loss | Pattern VEP | 26 out of 30 malingering cases showed normal VEP |
| Chouinard & Rouleau.25 | 1997 | Experimental | 73 | Suspected malingerers and controls | 48-Pictures Test, Rey Verbal Learning | 96% of malingerers were detected with this test |
| Gundogan et al.26 | 2007 | Case-control | 222 | Malingering military draftees, controls | Pattern VEP (PVEP) | Sensitivity 97.2%, specificity 62.5% for detecting malingering |
| Henry & Enders.27 | 2007 | Experimental | 60 | Malingerers vs. genuine patients | Continuous Visual Memory Test (CVMT) | 85% specificity for detecting malingering |
| Hamilton et al.28 | 2013 | Experimental | 36 | Children with suspected functional visual loss | Step VEP | Sensitivity 78%, specificity 100% |
| McBain et al.29 | 2007 | Observational | 100 | Patients with suspected non-organic vision loss | Pattern Appearance VEP | 100% of malingering cases identified with normal VEP |
| Rabiolo et al.30 | 2017 | Case-control | 30 | Malingering vs. maculopathy patients | Pattern VEP | Sensitivity 100%, specificity 94% for detecting malingering |
| Pouw et al.31 | 2017 | Experimental | 40 | Malingering colour vision loss | Colour Vision Test | Sensitivity 83%, specificity 94% for detecting malingering |
Notably, half of the included studies employed experimentally simulated malingering designs, while the remaining studies involved clinically suspected cases, which highlights an important distinction in study context.
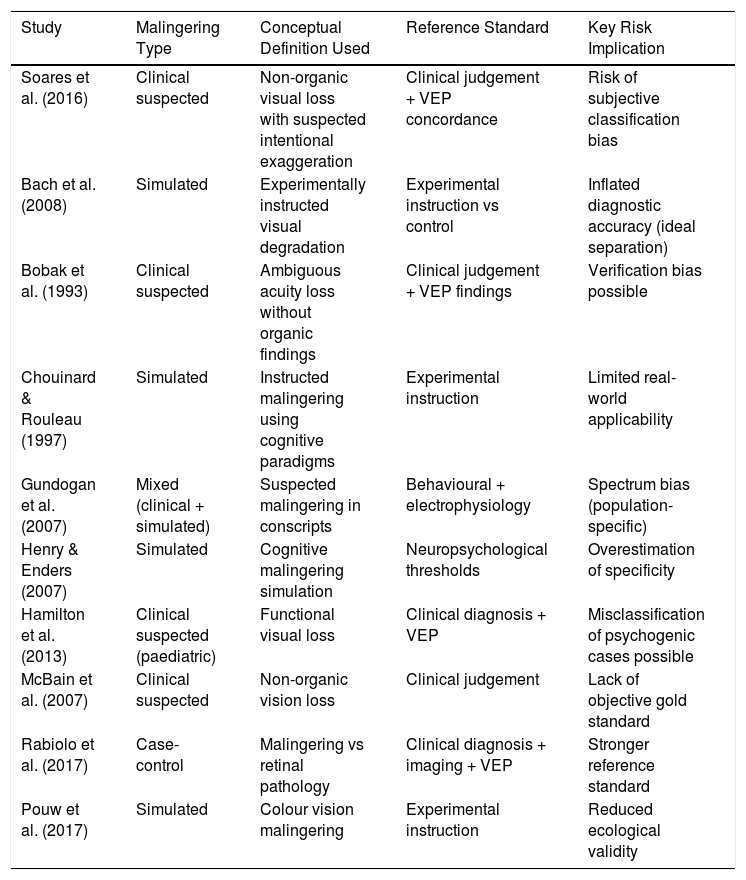
To complement the conceptual distinctions outlined in the introduction, Table 2 summarises the definitions of ocular malingering employed across studies, the type of malingering investigated (simulated versus clinically suspected), and the reference standards used. This highlights the heterogeneity in diagnostic frameworks and provides context for interpreting reported diagnostic accuracy estimates.
Conceptual definitions and reference standards across included studies.
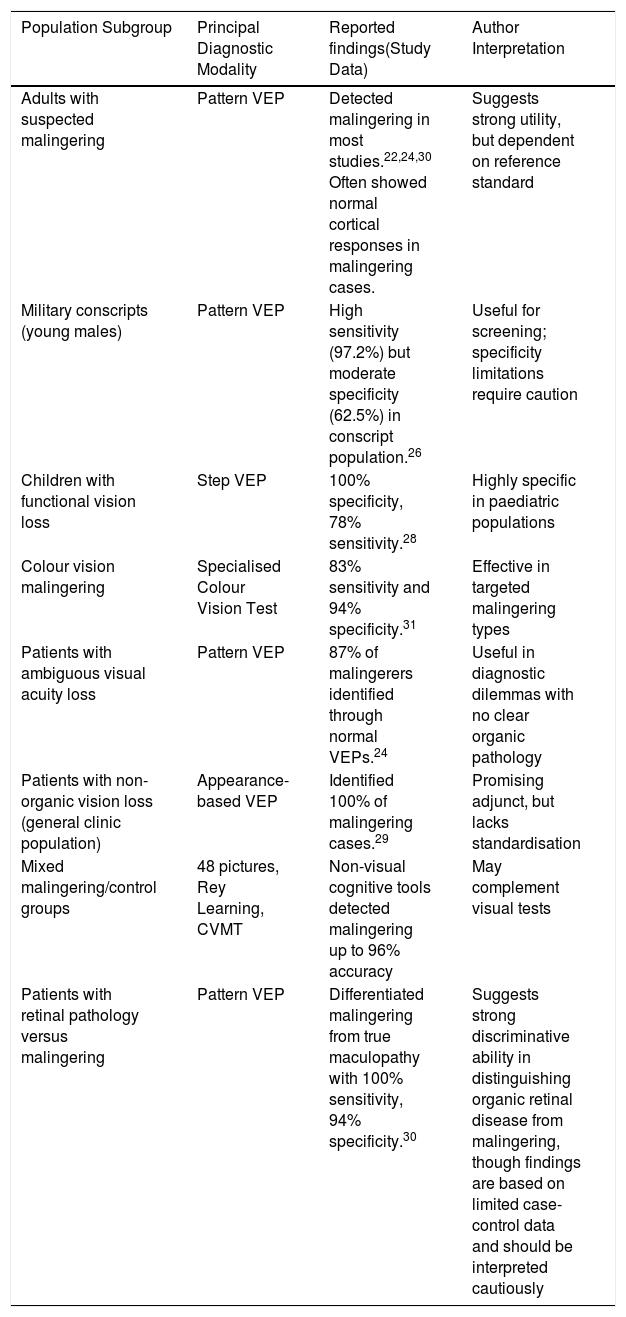
Although no formal statistical subgroup analysis was performed, thematic patterns emerged across the included studies. Table 3 summarises variations in diagnostic performance of objective tests according to the population subgroups, test types, and clinical contexts. Notably, pattern VEPs demonstrated consistently high sensitivity in adult and military populations, while step VEPs showed excellent specificity in paediatric cases. Colour vision tests and neuropsychological tools also performed well in targeted malingering scenarios.
Observed variations in diagnostic test performance by clinical subgroups.
| Population Subgroup | Principal Diagnostic Modality | Reported findings(Study Data) | Author Interpretation |
|---|---|---|---|
| Adults with suspected malingering | Pattern VEP | Detected malingering in most studies.22,24,30 Often showed normal cortical responses in malingering cases. | Suggests strong utility, but dependent on reference standard |
| Military conscripts (young males) | Pattern VEP | High sensitivity (97.2%) but moderate specificity (62.5%) in conscript population.26 | Useful for screening; specificity limitations require caution |
| Children with functional vision loss | Step VEP | 100% specificity, 78% sensitivity.28 | Highly specific in paediatric populations |
| Colour vision malingering | Specialised Colour Vision Test | 83% sensitivity and 94% specificity.31 | Effective in targeted malingering types |
| Patients with ambiguous visual acuity loss | Pattern VEP | 87% of malingerers identified through normal VEPs.24 | Useful in diagnostic dilemmas with no clear organic pathology |
| Patients with non-organic vision loss (general clinic population) | Appearance-based VEP | Identified 100% of malingering cases.29 | Promising adjunct, but lacks standardisation |
| Mixed malingering/control groups | 48 pictures, Rey Learning, CVMT | Non-visual cognitive tools detected malingering up to 96% accuracy | May complement visual tests |
| Patients with retinal pathology versus malingering | Pattern VEP | Differentiated malingering from true maculopathy with 100% sensitivity, 94% specificity.30 | Suggests strong discriminative ability in distinguishing organic retinal disease from malingering, though findings are based on limited case-control data and should be interpreted cautiously |
To further consolidate our understanding of the mechanisms by which objective diagnostic tests identify ocular malingering, a conceptual framework is presented in Fig. 2. This framework illustrates how such tests bypass conscious control and capture involuntary physiological responses.
Risk of bias assessment
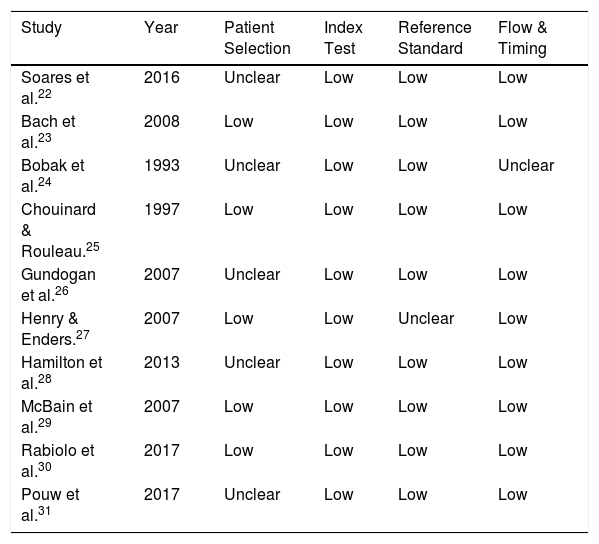
We evaluated the risk of bias using the QUADAS-2 tool across four domains. Most studies demonstrated low risk of bias in the reference standard and index test domains. Nevertheless, several studies were rated at unclear risk in the patient selection domain owing to issues with sampling methods or inclusion/exclusion criteria. Table 4 summarises the ratings for each study.
QUADAS-2 risk of bias assessment for included studies.
| Study | Year | Patient Selection | Index Test | Reference Standard | Flow & Timing |
|---|---|---|---|---|---|
| Soares et al.22 | 2016 | Unclear | Low | Low | Low |
| Bach et al.23 | 2008 | Low | Low | Low | Low |
| Bobak et al.24 | 1993 | Unclear | Low | Low | Unclear |
| Chouinard & Rouleau.25 | 1997 | Low | Low | Low | Low |
| Gundogan et al.26 | 2007 | Unclear | Low | Low | Low |
| Henry & Enders.27 | 2007 | Low | Low | Unclear | Low |
| Hamilton et al.28 | 2013 | Unclear | Low | Low | Low |
| McBain et al.29 | 2007 | Low | Low | Low | Low |
| Rabiolo et al.30 | 2017 | Low | Low | Low | Low |
| Pouw et al.31 | 2017 | Unclear | Low | Low | Low |
While the QUADAS-2 assessment indicated generally low risk of bias in the index test domain, important concerns were identified in the domains of patient selection and reference standards. Half of the studies22,24,26,28,31 were rated as having unclear or high risk of bias in patient selection due to non-random sampling, selective inclusion criteria, or the use of convenience samples. These factors may lead to spectrum bias, whereby the study population does not adequately represent the clinical population in which the diagnostic test would be applied.
Such biases have important implications for the interpretation of diagnostic accuracy estimates. In particular, studies involving well-defined groups (e.g., instructed simulators versus healthy controls) may overestimate sensitivity and specificity due to exaggerated separation between groups. This may partially explain the consistently high diagnostic performance reported in some experimental studies.
Additionally, concerns related to flow and timing were observed in some studies, including incomplete reporting of participant progression and lack of clarity regarding the temporal relationship between index tests and reference standards. These issues may introduce verification bias or misclassification, further affecting the reliability of reported outcomes.
These patterns suggest that the diagnostic accuracy of objective measures for detecting ocular malingering may be overestimated in some contexts.
DiscussionThis systematic review summarises existing evidence on the diagnostic accuracy of objective tests for detecting ocular malingering. The findings from this study agree with the use of objective tests particularly VEP, pupillometry, and eye-tracking technologies for differentiating true visual impairment from ocular malingering.13 VEP emerged as the most frequently applied and diagnostically reliable modality across studies as compared to other diagnostic modalities (Table 1). The consistently high sensitivity to VEPs may be due to their ability to bypass voluntary patient control, capturing cortical responses that malingering patients cannot manipulate.32,33 Pupillometry leverages the autonomic control of pupil dilation,34,35 which is difficult to consciously suppress or mimic, making it a valuable tool in distinguishing organic from non-organic vision loss.
A critical limitation identified in this review is the absence of a universally accepted gold standard for the diagnosis of ocular malingering. Across the included studies, a range of reference standards were employed, including clinical judgement, behavioural inconsistency criteria, experimental simulation paradigms, and neuropsychological thresholds. These approaches represent fundamentally different diagnostic targets, thereby introducing significant methodological heterogeneity.
The heterogeneity observed across studies, including variability in reference standards, study design, and population characteristics, has important implications for the interpretation of diagnostic accuracy metrics. Sensitivity and specificity estimates may not be directly comparable across studies due to differences in how malingering was defined and operationalised. Studies relying on clinical judgement are susceptible to subjective bias and potential misclassification, while those employing behavioural criteria may lack standardisation and reproducibility. These issues are further compounded by the use of experimentally simulated paradigms, which often involve instructed participants feigning impairment under controlled conditions in the absence of true pathology, thereby exaggerating diagnostic separation between groups. Additionally, spectrum bias may arise where study populations differ systematically, such as comparisons between clearly defined simulators and healthy controls versus clinically ambiguous cases. These factors suggest that reported diagnostic performance may be overestimated in certain contexts and should therefore be interpreted with caution.
As summarised in Table 2, substantial heterogeneity exists in both the definitions of malingering and the reference standards used across studies, reinforcing the need for cautious interpretation of pooled findings. A notable feature of the included literature is the substantial proportion of studies employing experimentally simulated malingering paradigms. In these designs, participants are instructed to feign visual impairment under controlled conditions, typically in the absence of underlying pathology, resulting in exaggerated or consistent behavioural patterns that are more readily detected by objective tests. In contrast, clinically suspected malingering occurs within more complex and heterogeneous contexts, often involving comorbidities, variable motivation, and inconsistent behavioural presentations. These differences have important implications for interpretation, as diagnostic accuracy estimates derived from experimental paradigms may not reflect real-world clinical performance and should not be directly extrapolated without caution.
Beyond the findings of the included studies, it is important to situate these results within the broader literature on malingering detection and electrophysiological validation. Traditionally, malingering has been identified through behavioural inconsistencies and symptom validity testing within neuropsychological and forensic contexts, emphasising performance patterns that deviate from known physiological limits. Objective ophthalmic measures, particularly VEP, extend this paradigm by providing physiologically grounded indicators that are less amenable to voluntary control. However, the detection of intentional deception remains inherently complex, as malingering involves behavioural and motivational dimensions that are not fully captured by electrophysiological responses alone.33 Accordingly, these tools should be conceptualised as adjunctive components within a multimodal diagnostic framework rather than definitive standalone measures.
This study also revealed that across the various patient subgroups and testing contexts, the diagnostic performance of the various tests varied. From Table 3, pattern-reversal VEPs were especially effective in adult populations36 and among military conscripts. On the other hand, in the paediatric population, step VEPs showed superior specificity, making them a valuable tool in children presenting with functional vision loss.37 Specialised colour vision tests also showed high diagnostic accuracy in cases of suspected colour vision malingering. It is worth noting that the findings from this study highlight the importance of selecting the right test modality for the suspected malingering type.
Again, from the risk of bias assessment using the QUADAS-2 tool (Table 4), the majority of the studies had low risk in the index test and the reference standard domain, while several others showed unclear or high risk in the patient selection domain. This finding reflects the variability in sampling methods and inclusion criteria, which may limit generalisability.
This study incorporated a thematic subgroup synthesis to capture the nuanced variation in test performance which is an important step in contextualising diagnostic tools in real-world settings.
Although the aim of this review was to systematically evaluate the diagnostic accuracy of objective measures for detecting ocular malingering, a meta-analysis was not feasible. This decision was informed by the wide heterogeneity observed across the included studies ranging from differences in study design (retrospective, observational, case-control, and experimental) to variations in the type of objective tests employed (pattern VEP, step VEP, pupillometry, colour vision testing, and neuropsychological tools), as well as the specific populations studied (children, adults, military conscripts, or simulated malingerers). Furthermore, the outcome metrics reported differed across studies, with some presenting sensitivity and specificity, while others focused on predictive values or diagnostic impressions without sufficient raw data for pooling. Given this level of methodological and clinical variability, any attempt to statistically synthesise the data would have undermined the internal coherence and interpretative value of the findings. A narrative synthesis, therefore, offered a more contextually faithful and clinically grounded approach to exploring the emerging patterns and implications of objective diagnostic tools in ocular malingering detection. While no meta-analysis was conducted, the consistency of high sensitivity and specificity across individual studies supports the reliability of these tests. Such findings suggest that objective diagnostic tests are promising tools for detecting ocular malingering.13
The findings of this review have important implications for both clinical practice and medico-legal evaluations. Clinicians assessing suspected ocular malingering can utilise objective tests such as VEP and pupillometry to assist in distinguishing malingering from genuine visual impairments. They may help reduce reliance on subjective symptom reporting and could potentiate targeted use of diagnostic investigations in selected clinical contexts.38
In medico-legal contexts, where visual complaints often underpin disability claims and legal evidence, objective measures may provide additional, physiology-based evidence to support clinical assessment.39 Hence, employing objective diagnostic tests in clinical and legal scenarios might improve the neutrality and correctness of decision-making.39 Finally, compared to subjective assessments, objective tests like ERG and eye-tracking offer higher reproducibility and standardisation, which is crucial in detecting malinger in legal contexts.4,40–42 These findings are consistent with the hypothesis that objective measures may aid in detecting ocular malingering.
The review, however, also noted some limitations of the available evidence. Because the primary literature often uses overlapping terms such as non-organic, psychogenic, functional, and malingering-related visual loss, some conceptual overlap across included studies is unavoidable. Also, variability in diagnostic accuracy likely reflects heterogeneity in study design, malingering types, and populations which makes pooled interpretation difficult. Again, most studies were assessed as having unclear risk of bias in the domain of patient selection, mostly due to variation in participant selection and assignment to groups. The methodological variation between the studies should be addressed in further studies to strengthen the evidence base. Also, the absence of standardised protocols and validation in different populations limits generalisability.
In conclusion, this systematic review demonstrates that objective diagnostic tools demonstrate promising utility as adjunctive measures in the assessment of ocular malingering. However, variability in study design and reference standards limits definitive conclusions regarding real-world diagnostic accuracy. These tools should therefore be interpreted cautiously and used to complement, rather than replace, comprehensive clinical assessment. By improving the accuracy of ocular malingering detection, there will be enhanced clinical decision-making by providing objective, reproducible diagnostic criteria based on a multimodal approach, reduced healthcare costs by minimising unnecessary referrals, tests and imaging procedures, improved occupational ocular assessments which will ensure that individuals with legitimate visual impairments receive appropriate support while preventing fraudulent claims and lastly, it will contribute to policy development, offering guidelines for vision assessments and insurance fraud in both occupational and clinical settings. Further studies are required to standardise testing protocols and address the heterogeneity observed across studies. Recent developments in machine learning–integrated eye-tracking technologies suggest that the future of malingering detection may shift toward real-time, clinic-friendly screening tools. These innovations hold promise for enhancing diagnostic objectivity and reducing the burden on clinician judgment, particularly in contexts where subjective reporting dominates the clinical narrative.
Declaration of generative AI and AI-assisted technologies in the manuscript preparation processDuring the preparation of this work the authors used ChatGPT in order to assist with language refinement, structural organization, and clarity of expression. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
FundingThe study received no funding.
The authors declare no competing interests.








