



This study compared the binocular and accommodative efficiency of young adults with myopic isometropia versus myopic anisometropia, difference spherical equivalent refraction (SER) ≥ 1.00 diopter (D), when corrected with ophthalmic versus contact lenses.
MethodsSeventy-two participants were categorized into isometropic (n = 36; age 21.92 ± 3.21 years) and anisometropic (n = 36; age 21.44 ± 2.62 years) myopia groups. Binocular and accommodative parameters were clinically evaluated under both ophthalmic and contact lens correction.
ResultsOphthalmic lens correction produced no significant differences (p > 0.05) in binocular visual efficiency between the two groups. Conversely, contact lens correction elicited distinct alterations in accommodative and vergence profiles. Myopic anisometropia showed a highly significant increase in accommodative lag when using contact lenses (p < 0.001) and increased negative relative accommodation (p = 0.007) compared to ophthalmic lenses. Furthermore, contact lenses amplified the fusional divergence demand to compensate for esophoria, thereby diminishing the near negative fusional vergence reserve (p = 0.012). Notably, contact lens wear was associated with better stereoacuity compared to ophthalmic lenses, which suggests a potential functional advantage in stereopsis for higher degrees of anisometropia, though this warrants further exploratory validation.
ConclusionIn conclusion, while contact lenses distinctly alter accommodative and vergence dynamics, they may offer functional advantages in stereopsis for higher degrees of anisometropia. These comparative insights provide valuable clinical guidance for selecting refractive correction modalities to support specific binocular functions and stereoscopic performance.
Anisometropia is defined as an interocular difference in refractive error originating from discrepancies in either axial length or refractive power.1 In clinical settings, an interocular difference in spherical equivalent refraction (SER) of ≥1.00 diopter (D) serves as the standard diagnostic criterion.2–4 This condition frequently co-occurs with myopia.5 Consequently, myopic anisometropia has become a highly prevalent clinical presentation, affecting up to 10% of the young adult population.1 The unequal refractive status inherent in anisometropia is a primary etiology of amblyopia.6 It causes continuous unilateral retinal blur, prompting the visual cortex to preferentially process the clearer image while suppressing the blurred one.7 Furthermore, even in the absence of amblyopia, myopic anisometropia severely compromises binocular vision due to aniseikonia—a clinically significant inequality in retinal image sizes. This disparity degrades fusional ability, leading to diplopia, visual suppression, and diminished stereopsis.8–10 Consequently, affected individuals frequently experience asthenopia, headaches, and impaired depth perception during demanding visual tasks, which substantially deteriorates their daily visual quality.11 Currently, spectacles (ophthalmic lens) and contact lenses remain the primary modalities for refractive correction.12 However, these approaches exert distinct physiological effects on binocular interaction. Ophthalmic lenses sit at a vertex distance of 12 to 14 millimeters13 which exacerbates aniseikonia by inducing inherent optical magnification differences.14 Additionally, during near-vision tasks, minus ophthalmic lenses induce a base-in prismatic effect. Conversely, contact lenses eliminate the vertex distance and this associated prismatic effect.15 Selecting the optimal corrective modality is therefore critical to restoring binocular harmony. However, current literature reveals a paucity of robust evidence comparing the specific accommodative and vergence effects of ophthalmic versus contact lenses in young adults with myopic anisometropia. To address this clinical gap, this study investigated the optimal refractive management strategy by comprehensively comparing binocular and accommodative functions under ophthalmic versus contact lens wear in young adults with myopic anisometropia and myopic isometropia.
Material and methodsStudy design and ethical considerationsThis prospective comparative study was conducted at the Optometry Clinic, Department of Optometry, Faculty of Allied Health Sciences, Naresuan University, from November 2025 to March 2026. The study protocol was approved by the Naresuan University Institutional Review Board (COA No. 373/2025) and registered with the Thai Clinical Trials Registry (Identifier: TCTR20251212010). All participants provided written informed consent prior to enrollment, in accordance with the Declaration of Helsinki.
Participant selectionHealthy male and female participants aged 18 to 35 years were recruited for this study. Eligible participants were required to have a myopic refractive error ranging from −0.50 to −6.00 D, astigmatism of ≤1.00 D, and a best-corrected visual acuity (BCVA) of 20/25 or better in both eyes at distance and near. Prior experience with ophthalmic or contact lens wear was not restricted. Participants were classified into two groups based on their interocular difference SER: (i) an isometropic myopia group (difference SER < 1.00 D) and (ii) a myopic anisometropia group (difference SER ≥ 1.00 D). Exclusion criteria included manifest strabismus (tropia), a history of ocular surgery, and any systemic or ocular conditions affecting vision (e.g., diabetes, cataracts, glaucoma). Furthermore, individuals with ocular surface anomalies contraindicating contact lens wear—such as severe dry eye, reduced corneal sensitivity, active conjunctivitis, pterygium, pinguecula, or incomplete blinking—were excluded.
Procedure and data collectionAll clinical assessments were conducted under SER-based refractive correction, ensuring a BCVA of 20/25 or better. To control diurnal variations, testing was performed over two separate visits scheduled. The first visit evaluated visual parameters using ophthalmic lens correction, while the second visit utilized contact lens correction by a single optometrist at the same time of day. Participants were fitted with daily disposable soft contact lenses (1-Day ACUVUE® MOIST; Johnson & Johnson Vision Care, Jacksonville, FL, USA) which made of etafilcon A hydrogel material and participants were allowed a 10 min adaptation period before testing. This interval also served to monitor for any adverse symptoms such as severe irritation, conjunctival injection, or epiphora. Participants underwent a comprehensive clinical evaluation comprising preliminary tests, interpupillary distance (PD) and visual acuity (VA) at distance and near, and comprehensive subjective refraction, followed by an extensive binocular and accommodative assessment. Manifest subjective refraction was performed without cycloplegia to preserve the natural accommodative state required for subsequent binocular and accommodative assessments. To effectively control accommodation and prevent over-minusing in this young adult cohort, standard binocular fogging techniques (Maximum Plus to Maximum Visual Acuity, MPMVA) were strictly applied. Specific parameters measured included stereoacuity using the Stereo Fly Test, phoria, vergence, accommodative convergence to accommodation (AC/A) ratios (gradient and calculated), binocular cross-cylinder (BCC), BCC testing was conducted using the standard cross-cylinder grid target positioned on a near-point rod at 40 cm and was performed in a dimly lit examination room, with the near target specifically illuminated by a head-mounted lamp. These identical lighting conditions were strictly maintained for all participants to prevent illumination-induced variations in accommodative responses, negative and positive relative accommodation (NRA and PRA), amplitude of accommodation (AA) using minus-lens-to-blur method, and both accommodative and vergence facilities. The measurements of all parameters were following the recommendations of Clinical Management of Binocular Vision by Scheiman and Wick.16 To study the relationship between the degree difference of SER and stereoacuity under different corrective conditions, this study categorized 36 participants in myopic anisometropia group into 3 categories based on myopia severity of each eye (myopia based on the classification criteria established by the International Myopia Institute (IMI);17 mild myopia ranging from −0.50 D to −2.75 D and moderate myopia ranging from −3.00 D to −6.00 D). Three categories including (i) Mild/Mild, (ii) Mild/Moderate, and (iii) Moderate/Moderate. This study then further subdivided them by the magnitude of anisometropia (Difference SER < 1.50 D vs. ≥1.50 D) into 6 groups (group A−F).
Statistical analysisStatistical analyses were performed using SPSS version 27.0 (SPSS Inc., Chicago, IL, USA). Continuous variables are expressed as mean ± standard deviation (SD). For comparative analyses between two independent groups, the Independent Samples t-test was used for normally distributed data, while the Mann-Whitney U test was applied for non-normally distributed data. For comparisons involving three or more groups, a One-way ANOVA was utilized for normally distributed data, whereas the Kruskal-Wallis H test was employed for non-normally distributed data. A p-value of <0.05 was considered statistically significant. The primary outcomes (stereoacuity, accommodative lag, negative relative accommodation, and fusional vergence parameters) were predefined a priori. Subgroup analyses based on anisometropia severity (Groups A–F) were strictly exploratory and intended to generate hypotheses. Due to the hypothesis-driven nature of the primary outcomes, formal multiplicity correction was not applied, and borderline p-values should be interpreted with caution.
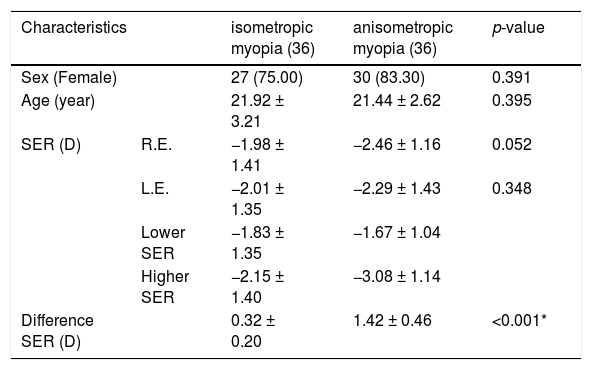
ResultsDemographic dataThis study evaluated two distinct cohorts: an isometropic myopia group and an anisometropic myopia group. A total of 72 participants were enrolled in the study and equally divided into two groups of 36 individuals. The isometropic myopia group comprised 27 females (75.0%) and 9 males (25.0%), with a mean age of 21.92 ± 3.21 years. The anisometropic myopia group consisted of 30 females (83.3%) and 6 males (16.7%), with a mean age of 21.44 ± 2.62 years. Comparison of baseline demographics revealed no statistically significant differences between the two groups regarding sex distribution (p = 0.391) and age distribution (p = 0.395). Furthermore, there were no significant differences in the refractive errors of the right and left eyes between the two groups (p = 0.052 and p = 0.348, respectively).
Regarding the specific refractive profiles of the isometropic and anisometropic groups, the mean lower SER were −1.83 ± 1.35 D and −1.67 ± 1.04 D, respectively, while the mean higher SER were −2.15 ± 1.40 D and −3.08 ± 1.14 D, respectively. As expected, the interocular difference in refractive error between the two groups was highly statistically significant (p < 0.001), as detailed in Table 1.
Characteristics of participants.
| Characteristics | isometropic myopia (36) | anisometropic myopia (36) | p-value | |
|---|---|---|---|---|
| Sex (Female) | 27 (75.00) | 30 (83.30) | 0.391 | |
| Age (year) | 21.92 ± 3.21 | 21.44 ± 2.62 | 0.395 | |
| SER (D) | R.E. | −1.98 ± 1.41 | −2.46 ± 1.16 | 0.052 |
| L.E. | −2.01 ± 1.35 | −2.29 ± 1.43 | 0.348 | |
| Lower SER | −1.83 ± 1.35 | −1.67 ± 1.04 | ||
| Higher SER | −2.15 ± 1.40 | −3.08 ± 1.14 | ||
| Difference SER (D) | 0.32 ± 0.20 | 1.42 ± 0.46 | <0.001* | |
SER: spherical equivalent refraction; D: Diopter; R.E.: right eye; L.E.: left eye.
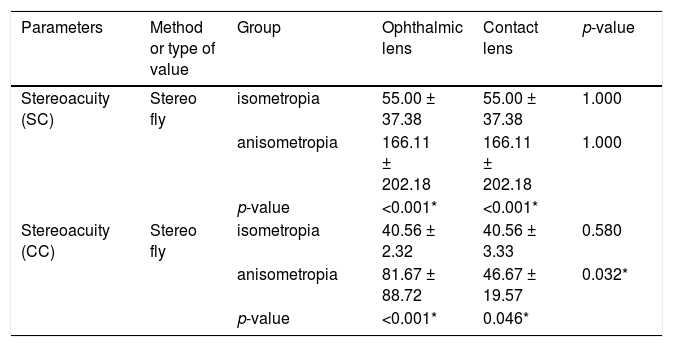
The comparative analysis of stereoacuity thresholds between the isometropic and anisometropic myopia groups revealed distinct differences based on both the refractive condition and the method of correction. In the uncorrected state (SC), the isometropic myopia group exhibited significantly lower stereoacuity thresholds (better depth perception) compared to the anisometropic myopia group. The isometropic group achieved a mean threshold of 55.00 ± 37.38 sec of arc, whereas the anisometropic group demonstrated a significantly higher mean threshold of 166.11 ± 202.18 sec of arc (p < 0.001). Following refractive correction (CC), both groups showed a marked reduction in stereoacuity thresholds; however, the efficacy of the correction modality varied by group. Isometropic myopia group no statistically significant difference was observed between correction methods (p = 0.580). Thresholds were nearly identical for ophthalmic lenses (40.56 ± 2.32 sec of arc) and contact lenses (40.56 ± 3.33 sec of arc), respectively. Anisometropic group, a marginal difference in performance was identified between the two correction methods (p = 0.032). While ophthalmic lenses improved stereoacuity to 81.67 ± 88.72 sec of arc, contact lens correction yielded a superior result of 46.67 ± 19.57 sec of arc. Furthermore, the difference in stereoacuity between the isometropic and anisometropic groups remained statistically significant when using ophthalmic lenses (p < 0.001). However, this gap was narrowed considerably when using contact lenses (p = 0.046) (Table 2).
Stereoacuity performance under ophthalmic versus contact lens correction in isometropic and anisometropic myopia.
SC: refractive without correction; CC: refractive with correction
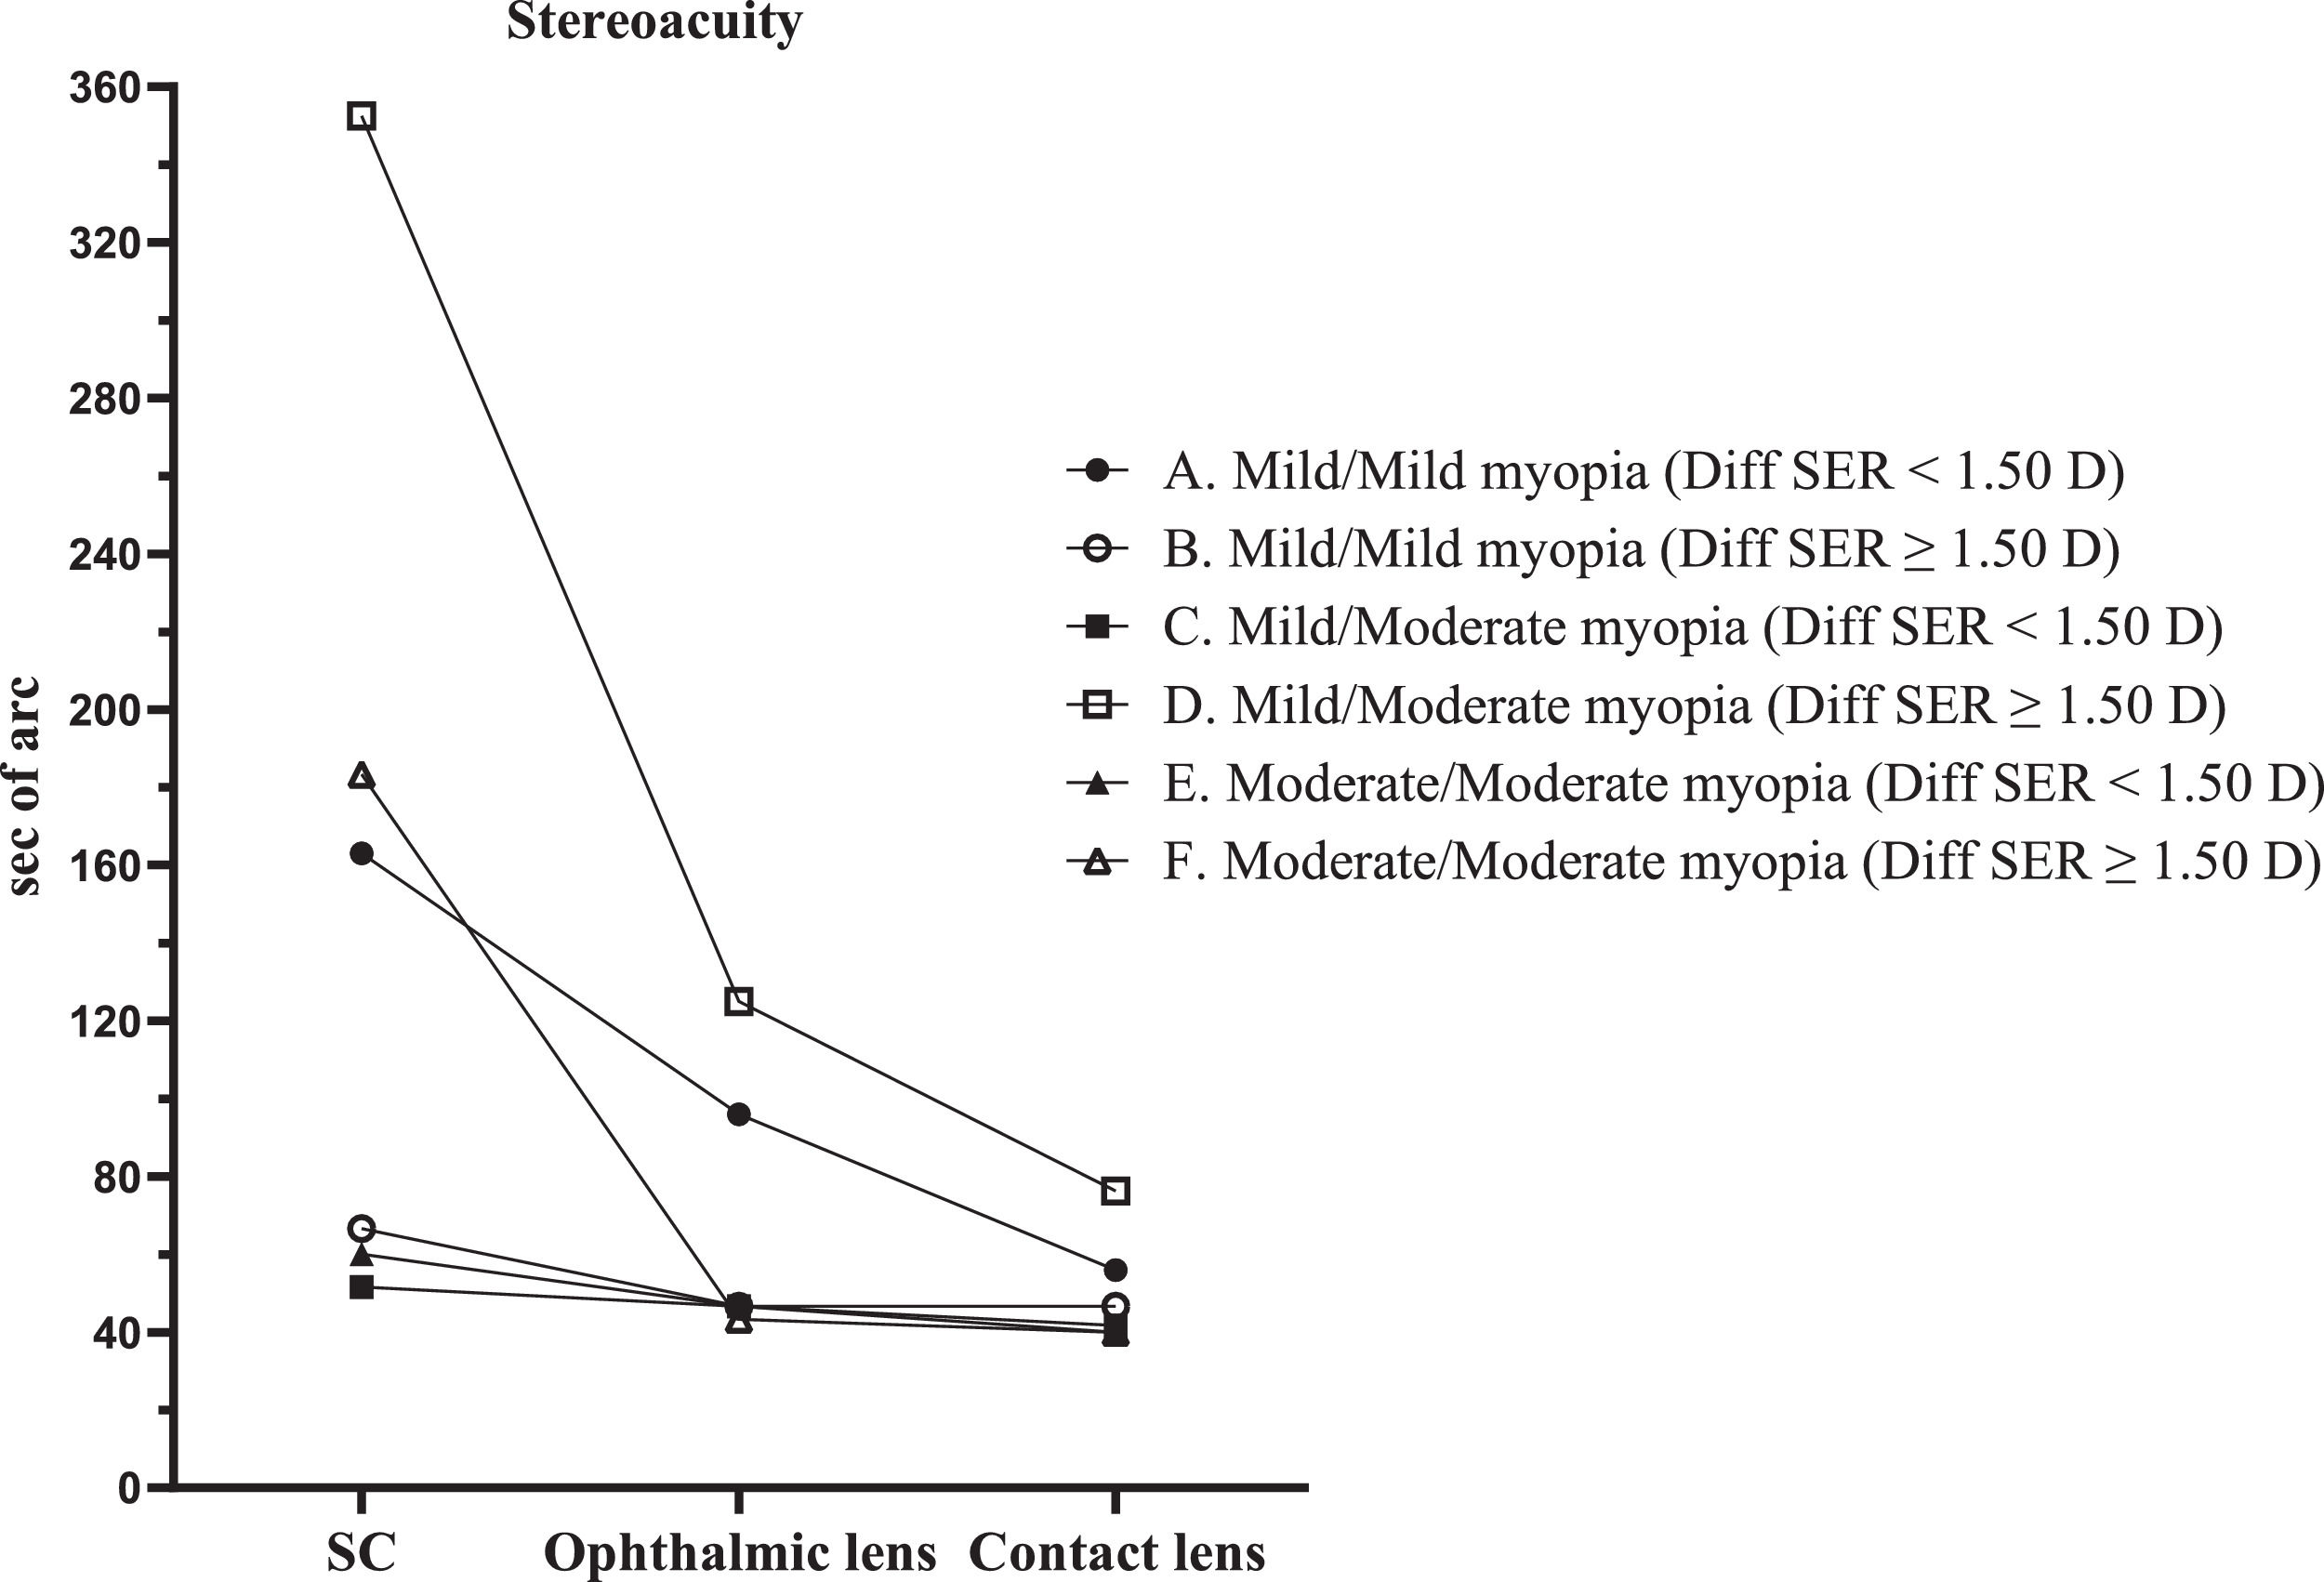
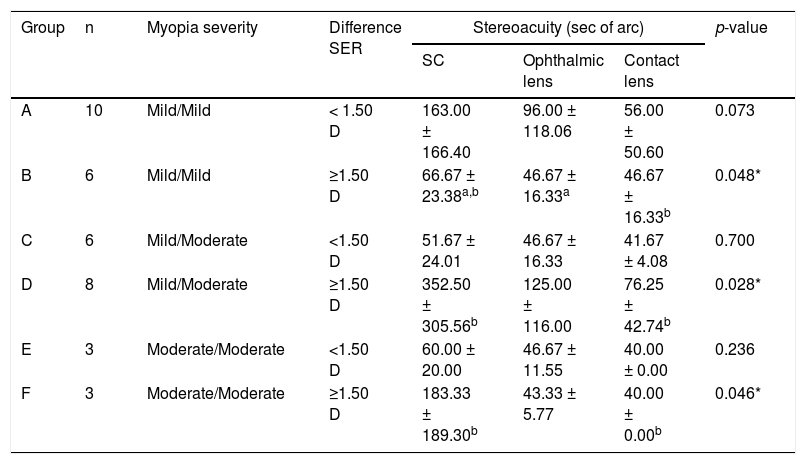
In low magnitudes of myopic anisometropia (Difference SER < 1.50 D), no statistically significant difference was found between ophthalmic lenses and contact lenses. Both correction methods successfully lowered stereoacuity thresholds to similar levels (group A, C, and E). However, high disparity groups (Difference SER ≥ 1.50 D) statistically significant differences between correction methods emerged when the SER difference was ≥1.50 D. In group B (Mild/Mild myopia) showed suggestive improvement with both methods, with a p-value of 0.048 indicating a preference for the corrected state over the uncorrected state, group D (Mild/Moderate myopia) contact lenses (76.25 ± 42.74 sec of arc) provided a potential advantage over ophthalmic lenses (125.00 ± 116.00 sec of arc) and group F (Moderate/Moderate myopia) contact lenses yielded a superior and more stable mean threshold of 40.00 ± 0.00 sec of arc compared to 43.33 ± 5.77 sec of arc for ophthalmic lenses (Fig. 1 and Table 3).

Comparative stereoacuity (sec of arc) between correction modalities stratified by baseline myopia and anisometropia severity.
Pairwise comparisons: a p < 0.05 for SC vs. ophthalmic lens; b p < 0.05 for SC vs. contact lens; D: Diopter; n: number; SC: without correction; * p < 0.05 by Kruskal-Wallis H test
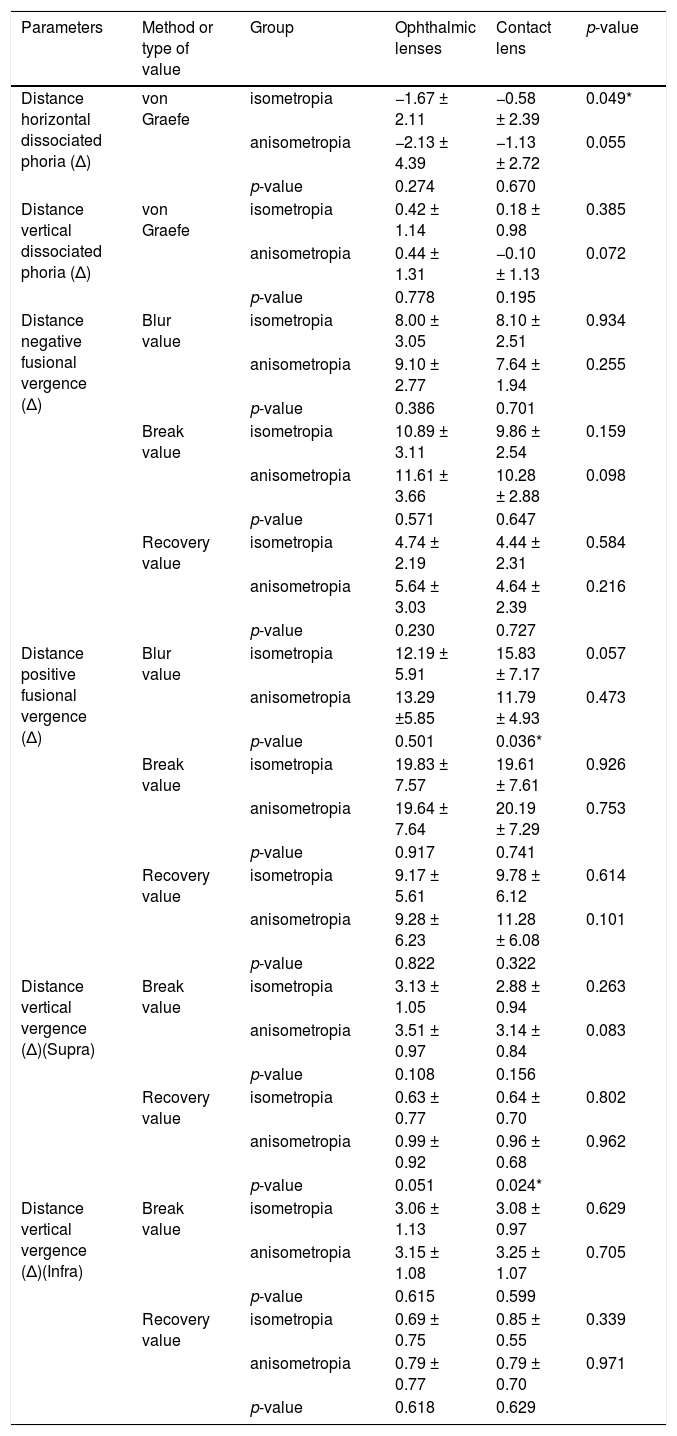
The assessment of binocular vision parameters, including dissociated phoria and fusional vergence at distance, revealed several statistically significant differences when comparing correction modalities and refractive groups (Table 4), including a borderline difference in distance horizontal dissociated phoria was observed within the isometropic myopia group based on the correction method (p = 0.049). No significant difference between correction methods was found in the anisometropic group (p = 0.055), the distance positive fusional vergence showed that the refractive group suggestively influenced the blur value during contact lens wear (p = 0.036), and distance vertical vergence (supra) significant inter-group difference was identified in the recovery value during contact lens correction (p = 0.024).
Distance binocular profiles (phoria and vergence) under ophthalmic versus contact lens correction in isometropic and anisometropic myopia.
∆: Prism Diopter
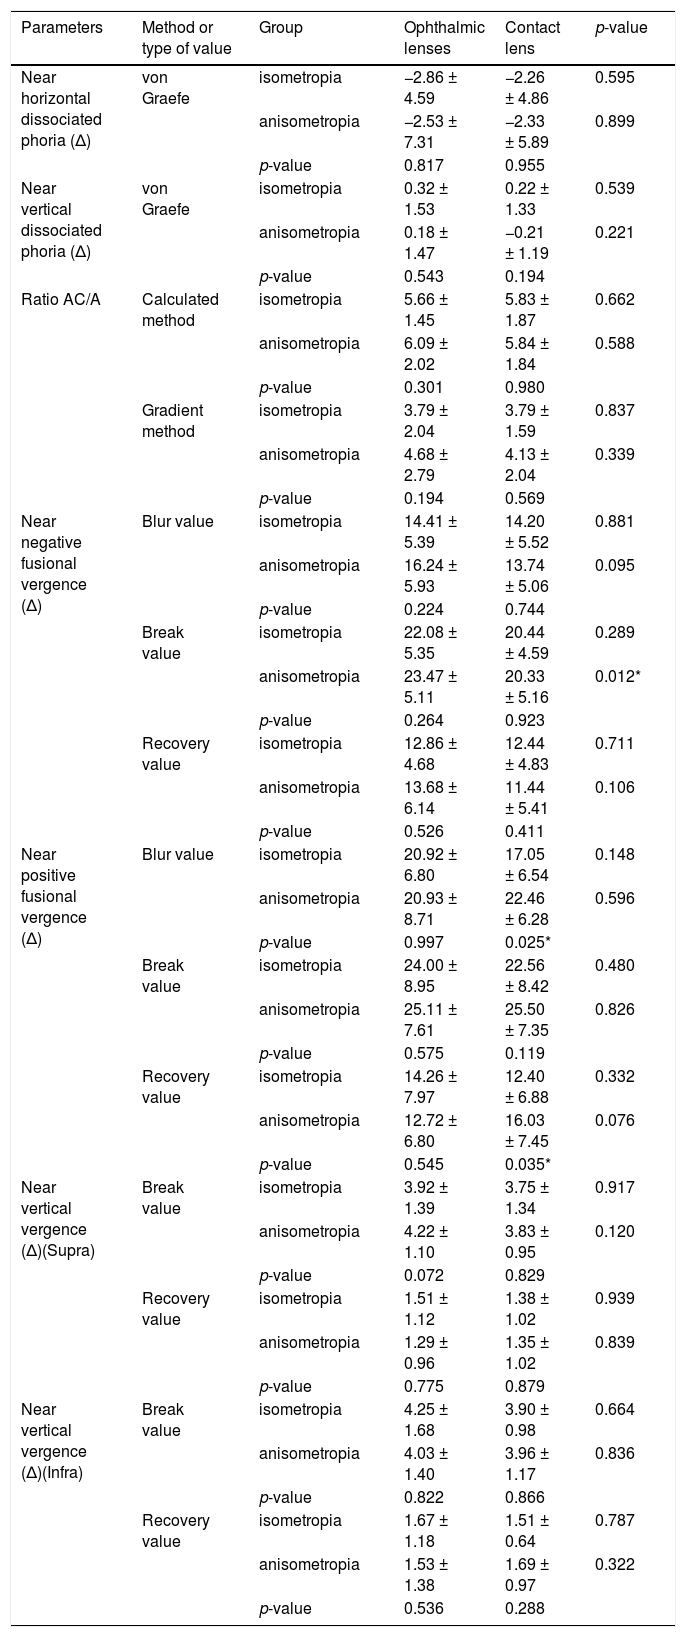
The assessment of binocular vision parameters at near distance revealed several statistically significant findings (p < 0.05) regarding fusional vergence ranges when comparing correction modalities and refractive groups (Table 5). In the anisometropic myopia group, a significant difference was observed in the break value between the two correction methods (p = 0.012), and near positive fusional vergence significant inter-group differences emerged during contact lens wear for both the initiation of blur and the recovery of fusion including blur value when using contact lenses, the anisometropic group exhibited a higher mean blur value (22.46 ± 6.28 ∆) compared to the isometropic group (17.05 ± 6.54 ∆) a significant difference was identified between refractive groups (p = 0.025), and recovery value during contact lens wear differed marginally between anisometropic group demonstrated a higher recovery capacity (16.03 ± 7.45 ∆) compared to the isometropic group (12.40 ± 6.88 ∆) (p = 0.035).
Near binocular and vergence dynamics under ophthalmic versus contact lens correction in isometropic and anisometropic myopia.
∆: Prism Diopter
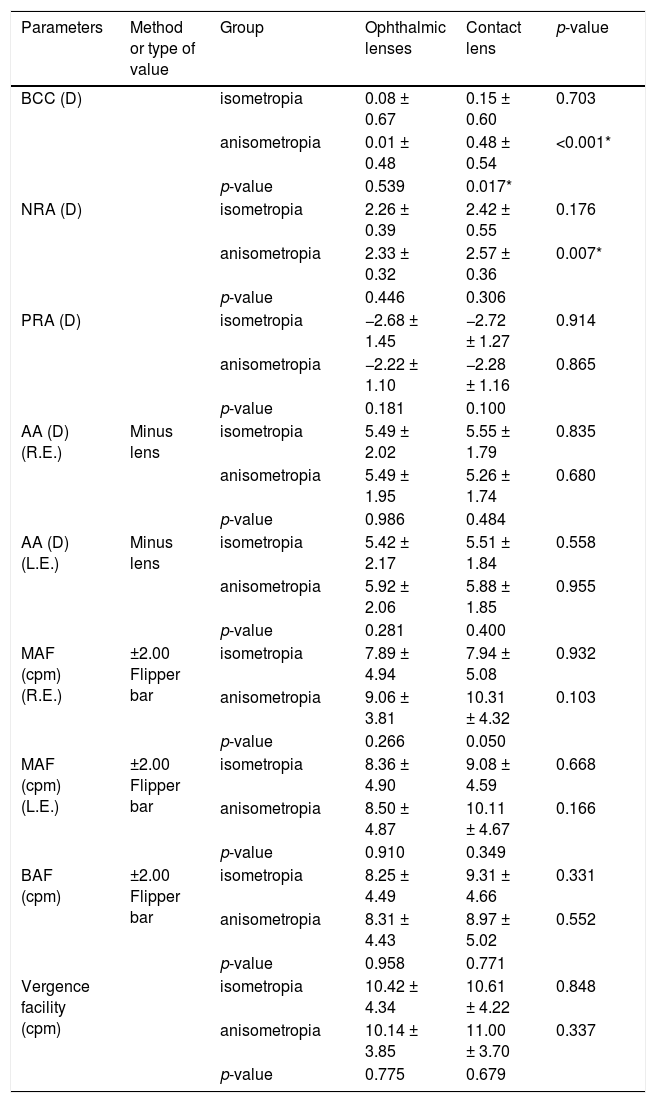
The analysis of accommodative function revealed significant differences primarily within the anisometropic myopia group and when comparing performance between refractive groups under contact lens correction. Regarding BCC, which measures accommodative lag, the anisometropic group showed a highly significant increase in lag when using contact lenses (0.48 ± 0.54 D) compared to ophthalmic lenses (0.01 ± 0.48 D; p < 0.001). Furthermore, when corrected with contact lenses, the anisometropic group exhibited a significantly greater accommodative lag than the isometropic group (0.48 ± 0.54 D vs. 0.15 ± 0.60 D; p = 0.017), whereas no such inter-group difference existed with ophthalmic lens use (p = 0.539). Additionally, the NRA was significantly higher for anisometropic subjects using contact lenses (2.57 ± 0.36 D) than when using ophthalmic lenses (2.33 ± 0.32 D; p = 0.007). In contrast, the isometropic myopia group maintained stable accommodative responses across both correction modalities, with no statistically significant differences observed in all parameters (Table 6).
Accommodative dynamics under ophthalmic versus contact lens correction in isometropic and anisometropic myopia.
BCC: Binocular cross cylinder; D: Diopter; NRA: Negative relative accommodation; PRA: Positive relative accommodation; AA: amplitude of accommodation; MAF: Monocular accommodation facility; BAF: Binocular accommodation facility; R.E.: right eye; L.E.: left eye; cpm: cycles per minute
The primary objective of this study was to compare binocular visual efficiency and accommodative dynamics under ophthalmic versus contact lens wear in young adults with myopic anisometropia and isometropic myopia. Our principal findings demonstrate a distinct clinical trade-off between the two correction modalities: while contact lenses induce specific near-point accommodative and vergence shifts, they afford significantly superior stereoscopic performance compared to ophthalmic lenses, particularly in individuals with moderate anisometropia (difference SER ≥ 1.50 D).
Stereoacuity represents the highest level of binocular visual processing, requiring precise cortical integration of disparate monocular inputs.18 In the uncorrected state, baseline stereopsis was profoundly degraded in the anisometropic cohort compared to the isometropic group (p < 0.001) (Table 2). This finding aligns with Khan et al., who demonstrated that anisometropic individuals exhibited significantly reduced stereopsis compared to isometropic and emmetropic subjects, with myopic anisometropia yielding the poorest stereoacuity.19 Furthermore, Oguz and Oguz reported that stereopsis degrades as the magnitude of anisometropia increases, noting that an interocular difference of 1.00 D or greater reduces stereoacuity by an average of 57 to 59 sec of arc. Thus, even low levels of anisometropia can significantly compromise binocular vision.20 The poorer uncorrected stereopsis observed in the anisometropic group may be explained by abnormal binocular visual development, in which unequal retinal input disrupts cortical binocular integration and leads to reduced stereopsis,21 confirming that even relatively low levels of interocular refractive differences severely disrupt binocular cortical pathways.19–21
Although ophthalmic lens correction restored stereoacuity to functional clinical ranges, the anisometropic group still exhibited lower performance than their isometropic peers. Crucially, as detailed in Fig. 1 and Table 3, contact lens correction yielded a statistically significant enhancement in stereoacuity over spectacles within the anisometropic group (p = 0.032). This clinical superiority is hypothesized to be primarily driven by the mitigation of aniseikonia; theoretically, contact lenses minimize the interocular retinal image size disparities inherently induced by the differential magnification of minus spectacle lenses, thereby facilitating robust binocular bifoveal fusion.21–23 Notably, our subgroup analysis revealed that for patients with an interocular SER difference of ≥1.50 D (Groups B and D), contact lenses showed a suggestive functional advantage, demonstrating marginal improvements in stereopsis than both the uncorrected and spectacle-corrected conditions (p = 0.048 and p = 0.028, respectively). This suggests that an interocular SER difference of ≥1.50 D may represent a hypothetical clinical point for supporting stereoscopic depth perception, which requires further longitudinal investigation. Clinically, this enhancement from gross to finer stereopsis translates to more precise binocular depth perception, which is crucial for fine motor tasks, hand-eye coordination, and navigating complex visual environments in daily life. In contrast to the distance parameters (Table 4) and vertical vergence profiles which remained highly stable across both refractive groups and correction methods, near-point binocular and vergence dynamics exhibited significant alterations under contact lens wear (Table 5). The anisometropic cohort experienced a distinct near esophoric shift when transitioning from spectacles to contact lenses. This phenomenon is theoretically rooted in the loss of the induced base-in (BI) prismatic effect that minus spectacle lenses naturally provide during convergence at near.15,24 By eliminating this spectacle-induced BI prism, contact lenses are thought to increase the active accommodative convergence demand. Consequently, this increased esophoric posture amplifies the compensatory fusional divergence demand, directly culminating in the observed significant reduction in the near negative fusional vergence break reserves (p = 0.012). Despite these near vergence stresses, positive fusional vergence and vergence facility remained intact, indicating that the overall fusional reserve capacity was compromised but not entirely destabilized.25
This optical-mechanical shift also directly modulated the accommodative profiles (Table 6). When wearing contact lenses, the anisometropic group demonstrated a significantly greater lag of accommodation (p < 0.001) and a concomitant elevation in NRA values (p = 0.007) compared to spectacle correction. The elimination of the spectacles' near BI prismatic effect effectively increases the objective accommodative demand at near, causing the accommodative system to operate with a larger steady-state error (greater lag) to maintain focus without over-expending energy.15 Importantly, because these accommodative lag values remained within acceptable functional norms (< +1.00 D),26 and dynamic accommodative facility was unaffected (p > 0.05), this shift represents a benign physiological adaptation rather than a pathological breakdown of the accommodative apparatus.15,27
Several limitations warrant consideration when interpreting these findings. Methodologically, the fixed, non-randomized testing sequence (ophthalmic lenses followed by contact lenses) introduces potential learning or practice effects, and the 10 min adaptation window restricts observations to acute physiological responses rather than long-term stability as longer adaptation may influence accommodative and binocular vision outcomes. Demographically, the cohort comprised exclusively young adults, limiting generalizability to presbyopic populations, and despite strict washout periods, prior contact lens experience may have influenced initial sensory adaptations compared to complete neophytes. Regarding the outcomes, while changes in accommodative lag and negative relative accommodation were statistically significant, their small absolute magnitudes may not meaningfully impact daily visual performance in asymptomatic individuals, though they remain relevant for patients with high visual demands, prolonged near work, or pre-existing binocular vision anomalies. In contrast, the observed stereoscopic improvements offer clearer functional relevance. Nevertheless, the absence of subjective symptom evaluations (e.g., asthenopia or visual comfort) leaves the real-world impact of these accommodative shifts unquantified, underscoring the need for future studies utilizing patient-reported outcome measures. Finally, the subgroup stratifications (Groups A−F) were strictly exploratory and hypothesis-generating; the small sample sizes in higher anisometropia cohorts (n = 3) restrict statistical power and increase the risk of Type II errors. Consequently, these specific observations should be interpreted with clinical caution and not dictate definitive thresholds until validated by larger, adequately powered longitudinal trials.
Taken together, these findings provide valuable clinical insights for the management of myopic anisometropia. While spectacles offer a conventional correction that preserves near vergence and accommodative reserves, they may limit stereoscopic performance in patients with interocular SER differences ≥1.50 D. For these patients, contact lenses may offer functional advantages in supporting binocular integration and stereopsis, provided that clinicians monitor and manage the potential increase in near esophoria and reduced negative fusional vergence reserves. If visual symptoms arise, these accommodative and vergence shifts can be managed appropriately through targeted visual hygiene or vision therapy.
ConclusionThe modality of refractive correction fundamentally alters binocular and accommodative dynamics in myopic anisometropia. While ophthalmic lenses uniformly preserve baseline binocular functions across myopic profiles, contact lenses elicit distinct physiological shifts. Specifically, the optical removal of the near base-in prismatic effect with contact lenses is proposed to increases accommodative demand, manifesting clinically as a greater accommodative lag and higher NRA. Furthermore, contact lenses induce a near esophoric shift, amplifying the fusional divergence demand and consequently diminishing the negative fusional vergence reserve.
Despite these accommodative and vergence alterations, contact lens wear was associated with better stereoacuity compared to ophthalmic lenses, theoretically driven by the hypothesized mitigation of aniseikonia. Therefore, while both modalities are clinically viable, contact lens correction suggests potential functional advantages in stereoscopic performance for higher degrees of myopic anisometropia (e.g., ≥1.50 D), though this exploratory finding warrants further investigation. Ultimately, these findings elucidate the clinical differences between refractive modalities, providing valuable clinical insights for the assessment, management, and follow-up of myopic anisometropia to support specific binocular functions and stereoscopic integration. However, given the limited sample sizes in certain subgroup analyses, these specific findings should be considered strictly exploratory and hypothesis-generating. Future longitudinal studies utilizing larger clinical cohorts, longer adaptation periods, and patient-reported outcome measures are necessary to comprehensively explore the long-term physiological trends and conclusively validate these observations.
FundingThis work was partially supported by Frontier Research and Innovation Cluster Fund, Naresuan University [Grant number R2569C006]. The sponsor provided financial support for the conduct of the research in the writing of the manuscript.
Authors’ contributionsConceptualization and design of the study, acquisition of data, analysis and interpretation of data and drafting the article, A.D., B.S., C.K., M.S., W.K., and S.W.; writing—review and editing, A.D., and S.W.; visualization and funding acquisition, S.W.; supervision and project administration, A.D., and S.W. All authors have read and agreed to the published version of the manuscript.
Declaration of generative AI and AI-assisted technologies in the manuscript preparation processDuring the preparation of this work the authors used Gemini 3.1 Pro in order to improve readability and especially improve language in drafting this paper in English. After using this tool/service, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
None.
The authors gratefully acknowledge all the facilities of the Department of Optometry, Faculty of Allied Health Sciences, Naresuan University, Thailand. The authors also thankfully acknowledge the thesis funding support for the academic year 2025 from the Faculty of Allied Health Sciences, Naresuan University, Thailand. S.W. thankfully acknowledges funding from Frontier Research and Innovation Cluster Fund, Naresuan University; Grant number R2569C006.







